What Is the Anion Gap?
The anion gap is a calculated value that helps assess acid-base status by examining the main measured electrolytes in a blood sample. It is typically calculated from a serum chemistry panel or other serum electrolytes results, using the relationship between sodium, chloride, and bicarbonate. Clinically, it helps identify whether there are unmeasured anions contributing to an anion deficit and an underlying acid-base disorder.
In simple terms, the anion gap is a diagnostic tool that measures the difference between positively charged and negatively charged particles in the blood. That difference reflects electrolyte balance and can point to a metabolic disturbance that is not obvious from the individual values alone. Because it is based on routine blood chemistry, it is often used anion gap as a screening test during patient assessment.
Most modern labs provide the ingredients needed for the calculation as a standard laboratory result. Even though the concept sounds abstract, the practical use is straightforward: if the gap is elevated, clinicians think about causes of metabolic acidosis, especially high anion gap metabolic acidosis.
Anion Gap Formula Without K
The standardly used calculation formula without potassium is as follows:
Anion gap = sodium - (chloride + bicarbonate)
This formula uses sodium level, chloride value, and serum bicarbonate values from the lab. If you're using an Anion Gap Calculator, this is typically the default method because it is easier and matches common clinical practice.
All values are typically reported in mEq/L. The formula takes away the total of chloride and bicarbonate from sodium. Since sodium is the primary measured cation in the panel, and chloride plus bicarbonate are the main measured anions, the result approximates the space left by negative charge from unmeasured substances.
Even though some older formulas also included potassium, many clinicians omit it because the contribution is small and does not usually change the practical medical interpretation. A simplified formula makes the calculation more convenient without sacrificing much utility in routine use.
When checking the result manually, make sure the units are consistent and that the numbers come from the same laboratory values set. An error in units or transcription can alter the result significantly.
Step by Step Computing Illustration
Below is a simple worked example with typical lab values:
- Na = 140 mEq/L Cl = 102 mEq/L Bicarbonate = 24 mEq/L
With the calculation:
Anion gap = 140 - (102 + 24)
First combining chloride and bicarbonate:
102 + 24 = 126
Next deduct from sodium:
140 - 126 = 14
This value is 14 mEq/L. Based on the lab normal range, this may be considered normal or mildly elevated. For that reason the result must always be interpreted in context rather than as a stand-alone number.
Relying on an anion gap calculator can reduce arithmetic mistakes, but the manual method is easy to confirm. The key is to remember the exact equation and to use current lab values rather than outdated results. When values change rapidly, the gap can shift along with the patient’s blood acid-base status.
Standard Range and Meaning
A expected anion gap depends on the laboratory reference range, the measurement method, and whether potassium is included. In many settings, a typical non-potassium result is roughly in the low teens, but the exact normal interval differs from one lab to another. Always compare the number with the lab’s stated range instead of relying on a universal cutoff.
A high anion gap suggests extra unmeasured acids in the blood. This pattern is commonly associated with acidosis, especially high anion gap metabolic acidosis. The finding can help narrow the differential diagnosis, but it does not identify the cause by itself.
One important factor is albumin. Because albumin is a major unmeasured anion, low albumin can make the anion gap appear lower than expected. In those cases, clinicians may use an corrected anion gap to get a more accurate corrected value. This is especially useful when evaluating a suspected acid-base disorder in patients with hypoalbuminemia.
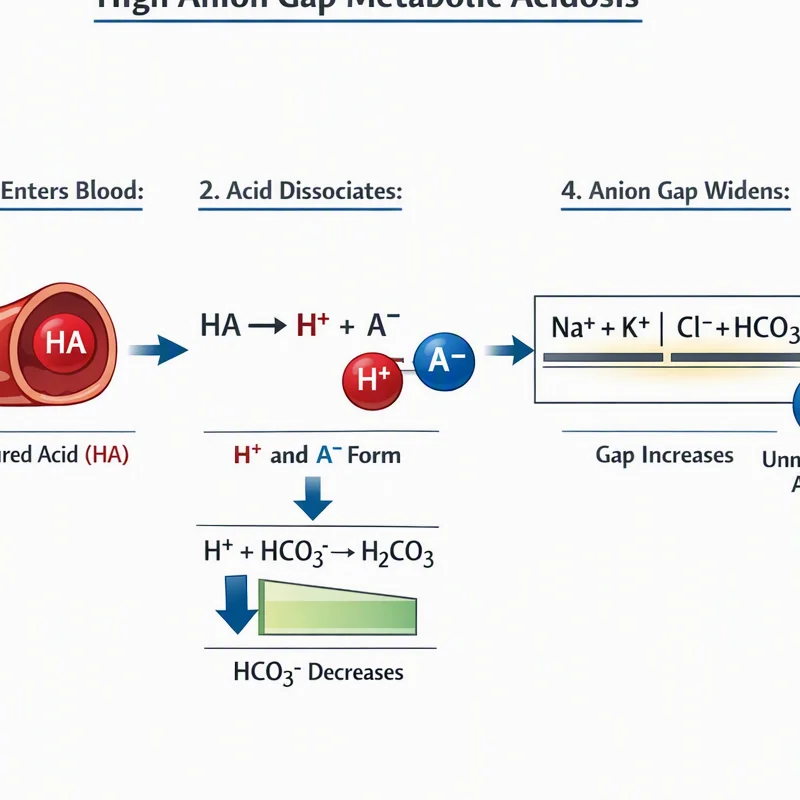
Interpretation should also distinguish high-gap from normal anion gap metabolic acidosis. A normal gap does not rule out acidosis; it may indicate bicarbonate loss with a compensatory rise in chloride, as seen in normal-gap patterns. That is why the number should always be viewed alongside the full chemistry panel and the broader clinical picture.
How come Potassium Is Often Left Out
Potassium is often excluded because its concentration is much lower than sodium, and the difference usually has limited impact on everyday clinical practice. The simplified formula enhances consistency and speeds up use in busy settings. Many forms of laboratory reporting also leave out potassium for this reason.
From a practical standpoint, leaving potassium out makes the calculation easier to remember and lowers the chance of error. The change in result is often minor enough that it does not change the general conclusion, especially when the goal is basic screening rather than highly specialized analysis.
That said, the omitted-potassium method is not a different concept. It is the same physiologic idea, just a simplified approach built into many calculators and lab systems. If an older source includes potassium, the resulting number will be marginally higher, but the overall assessment of acid-base status often stays similar.
In other words, the anion gap calculator commonly used in practice is based on the abbreviated formula because it is effective, reproducible, and sufficient for most patient assessment scenarios.
Origins of a Elevated Anion Gap
A raised result suggests additional acid or unmeasured anions in the bloodstream. Typical causes include lactic acidosis, ketoacidosis, renal failure, and toxic ingestions. Each of these can elevate the gap for a distinct reason, but all lead to an increase in hidden acids.
Lactic acidosis occurs when lactate accumulates, often in situations of poor perfusion, severe illness, or impaired oxygen delivery. Ketoacidosis occurs when ketones accumulate, such as in diabetes or prolonged fasting. Renal failure can reduce acid excretion, allowing acids to build up. Toxic ingestions may expose the body to substances that are metabolized into acids or that interfere with normal metabolism.
These causes are especially important when the anion gap is elevated alongside signs of metabolic acidosis. A clinician may use the gap as a clue, then integrate it with history, physical findings, and additional testing to identify the underlying problem. The gap itself is a indicator, not a final diagnosis.
Because different disorders can produce the same pattern, the value should be considered part of a wider diagnostic framework. A patient with high-gap acidosis needs a targeted evaluation, and the anion gap calculator can help flag the issue early.
Constraints of the Anion Gap Calculator
An anion gap calculator is useful, but it has important restrictions. The primary is correction for albumin. Since albumin is a primary contributor to the normal gap, low albumin can obscure a clinically meaningful elevation. Without adjustment, the result may look inaccurately reassuring.
Second, the result depends on the laboratory’s reference range. Multiple techniques, analyzers, and reporting methods can yield different results, so a measurement that looks out of range in one lab may be normal in another. For this reason interpretation should always be tied to the particular laboratory’s reference interval.
Third, lab error may distort the outcome. Sample contamination, late analysis, or recording mistakes can change sodium, chloride, or bicarbonate values. Since the gap is derived from these components, even one inaccurate test result can lead to a misleading conclusion.
In the end, the formula is only part of the whole of the assessment. It does not take the place of a full clinical assessment, arterial or venous blood gas when needed, or evaluation for other sources of acid-base disturbance. Used properly, it is a useful screening measure; by itself, it can be limited.
Common Questions
How do you calculate anion gap without potassium?
Use the formula sodium - (chloride + bicarbonate). This anion gap calculatoranion gap is the common basic formula and is what how most anion gap calculator resources use. Type in the lab values in mEq/L and subtract the sum of chloride and bicarbonate from sodium.
Can you explain the formula for an anion gap calculator without potassium?
The formula is anion gap = sodium - (chloride + bicarbonate). It uses the primary serum electrolytes from the chemistry panel and omits potassium for simplicity. This is the most common calculation formula in regular use.
What is a normal anion gap when potassium is left out?
The expected values vary by the lab’s reference interval and testing method. Most laboratories consider a slightly elevated result normal when potassium is excluded, but you should always compare the number to the reported reference range on that specific laboratory result.
Why is potassium often left out of the anion gap calculation?
Potassium is usually excluded because it contributes minimally to the overall result. Leaving it out creates a simplified formula that fits common clinical practice and laboratory reporting standards without meaningfully changing everyday clinical interpretation.
What does a high anion gap mean clinically?
A high result suggests additional unmeasured acids and is often associated with acidotic states, especially elevated anion gap metabolic acidosis. Common causes include lactate buildup, ketosis-related acidosis, renal impairment, and poisoning. The value supports evaluation, but the cause requires further workup.