What the Anion Gap Measures
The anion-gap is a derived value used to aid interpret serum electrolytes and understand how the body is maintaining acid and base balance. An Anion Gap Calculator calculates the anion gap value from routine biochemistry values, usually sodium, chloride, and bicarbonate. This provides a practical tool for quick clinical interpretation of an chemistry panel.
The calculation helps spot whether there may be excess hidden anions in the blood. These are substances not directly shown on a standard blood chemistry report but that still influence the overall charge balance. When the gap is increased anion gap, it can point toward conditions such as metabolic acidosis. When it is low anion gap, it may suggest issues such as low albumin, laboratory problems, or other less common causes.
Because the anion gap is derived from everyday laboratory values, it is widely used as a checking and follow-up measure rather than a standalone diagnosis. It gives context to other findings and can help narrow the differential in an acid-base imbalance. In short, it is a simple way to calculate anion gap results and connect them to broader physiology.
Using the Anion Gap Calculator
Using an Anion Gap Calculator is straightforward. You enter the relevant input values from the laboratory report: serum sodium, serum chloride, and plasma bicarbonate. The tool then calculates with the anion gap formula and returns the calculator result.
Many calculators are designed for fast review of routine electrolytes. Some may also let you add albumin for a corrected anion gap, which can be helpful when protein levels are abnormal. This matters because albumin is one of the major unmeasured negatively charged substances in blood chemistry.
To use the calculator well:
- Enter the exact numbers shown on the lab report. Confirm the units match the calculator’s expected format. Determine whether the tool uses a standard or albumin-adjusted calculation. Review the normal range shown by the calculator or your lab source.
The result should be interpreted in context. A single number may look normal, but if the patient has symptoms or other abnormal lab values, the overall picture may still point to a clinically important problem. Likewise, a mildly abnormal result may be less concerning if it fits the expected picture of the patient’s condition.
Anion Gap Formula and Interpretation
The usual anion gap formula is expressed as Na minus Cl minus HCO3. Simply stated, it means subtracting chloride and bicarbonate from sodium. This straightforward formula calculates the balance between measured positive and negative ions in the blood.
The basic idea is that sodium is the main measured cation, while chloride and bicarbonate are the main measured anions included in the calculation. The gap represents the charge contributed by unmeasured ions. A within-range or normal anion gap points to a comparatively even pattern of measured and unmeasured ions, while a shift in either direction can reveal a hidden disturbance.
One important adjustment is albumin correction. Albumin contributes significantly to the anion gap because it carries negative charge. When albumin is low, the measured gap may appear artificially reduced. A corrected anion gap can therefore more closely match true physiology in certain patients.
An elevated anion gap often indicates increased unmeasured acids in the blood, which is a major clue in metabolic acidosis. A low anion gap is less common, but it can be clinically meaningful when it reflects hypoalbuminemia, excess positively charged proteins, or technical error.
View the anion gap as a clue rather than a diagnosis. It can help show whether the blood chemistry pattern suggests hidden acids, protein shifts, or a measurement problem.
Frequent Causes of a raised anion gap
A elevated anion gap usually indicates there are present extra acids or unmeasured anions in the bloodstream. This result is especially important in metabolic acidosis, where acid buildup lowers bicarbonate and changes the overall electrolyte picture.
Typical causes include:
- Lactic acidosis, where lactate rises because of poor oxygen delivery, shock, sepsis, or other stress states. Ketoacidosis, including diabetic ketoacidosis, alcoholic ketoacidosis, or starvation-related ketosis. Renal failure, where the kidneys cannot clear acids effectively. Toxic ingestion, such as exposure to substances that generate acid metabolites or interfere with normal metabolism.
These causes are important because they point to very different treatments. For example, lactic acidosis may require urgent stabilization and correction of the underlying cause, while ketoacidosis requires insulin, fluids, and careful electrolyte management. In renal failure, impaired acid elimination and electrolyte handling often drive the abnormal result. With toxic ingestion, the pattern may be a critical diagnostic clue.
The calculator result alone does not tell you which cause is present. It only highlights that there may be extra unmeasured anions, prompting further review of the patient’s symptoms, lab results, and acid-base status.
Common Causes of a Reduced Anion Gap
A reduced anion gap is rarer than a high one, but it can still matter. The leading explanation is hypoalbuminemia, since low albumin eliminates a major source of negative charge from the measured system. In many cases, this is why albumin correction is so helpful.
Additional common causes are:
- Lab error, which is always worth checking if the result does not align with the clinical picture. Paraproteinemia, where abnormal proteins contribute unusual positive charge patterns. Hyperchloremia, which can lower the calculated gap by shifting the relationship between sodium, chloride, and bicarbonate.
A low gap may also be seen when the measurement technique or specimen handling influences the reported values. Because of that, a repeat panel is sometimes needed before concluding that the result reflects a true disorder. Reviewing the reference range and the patient’s overall status helps determine whether the low result is clinically relevant.
When hypoalbuminemia is present, the apparent low gap may not indicate a true acid-base problem. Instead, the value may simply reflect reduced albumin concentration. That is why the serum anion gap should always be interpreted with the protein level in mind.
Limitations of the Calculator
An Anion Gap Calculator is useful, but it has specific limitations. Initially, the result depends on the precision of the entered lab values. If the sodium, chloride, or bicarbonate measurement is off, the calculated gap will also be inaccurate. Even small shifts in the input values can change the result.
Next, calculators may use marginally different reference range cutoffs depending on the laboratory or method. That means a value considered normal in one setting may be borderline in another. Some calculators also use different assumptions about whether potassium is included, which can alter the interpretation slightly.
Third, albumin can significantly affect the interpretation. A calculator that does not include albumin may fail to detect a true abnormality or make a low value look more worrisome than it is. A corrected anion gap can improve interpretation, but it still does not replace full clinical assessment.
Additionally, the anion gap is only one piece of the puzzle. It does not replace an arterial blood gas when a comprehensive evaluation of pH, carbon dioxide, and compensation is needed. It also does not identify the specific cause of an abnormality. It provides diagnostic support, not a final diagnosis.
In the end, the calculator must be interpreted in clinical context. Symptoms, medication history, kidney function, nutrition status, and other chemistry results all influence what the number means. A result can be unremarkable and still miss a developing problem, or it can be abnormal without indicating an emergency.
When to Seek Medical Interpretation
When the calculator shows a notable shift, medical review is advisable. An abnormal Anion Gap Calculator can signal an acid-base imbalance, especially if it is accompanied by low bicarbonate, abnormal pH, or alarming symptoms. This is particularly true when the pattern suggests metabolic acidosis.
Clinical interpretation is also valuable when there is a wider electrolyte imbalance. Because the result depends on the relationship among sodium, chloride, and bicarbonate, other disturbances in electrolyte balance can change the meaning of the number. A value that seems slightly abnormal may become more important if the person is dehydrated, critically ill, or has kidney dysfunction.
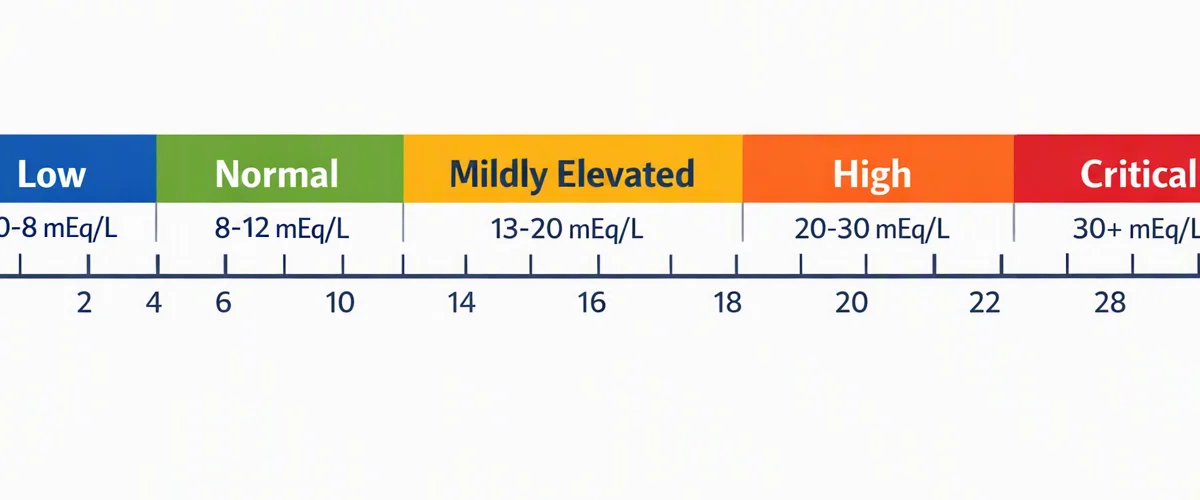
You should seek a healthcare provider for interpretation when:
- The value is obviously above or below the expected range. There are symptoms such as confusion, fast breathing, vomiting, weakness, or marked fatigue. The patient has diabetes, kidney disease, suspected poisoning, or another serious illness. The calculator suggests a elevated anion gap or low anion gap that does not match the clinical picture.
The anion gap in serum is most helpful when viewed as part of a fuller assessment. In practice, it often points to the next step: repeat testing, albumin adjustment, blood gas analysis, or investigation for a specific cause of acidosis or protein abnormality.
Frequently Asked Questions
What is a normal anion gap?
The anion gap normal range varies by testing method and the tool used. Many sources consider a usual result to sit within a relatively small expected range, but the precise cutoff should be taken from the laboratory report or the calculator itself. The most anion gap calculatoranion gap Anion-Gap-Calculation.com important point is to review the result with the range attached to the specific lab values being interpreted.
How do you calculate the serum anion gap?
You calculate the anion gap in serum using the gap formula: Na - Cl - HCO3. In real use, you type in the measured serum sodium, serum chloride, and HCO3 into an Anion Gap Calculator. The calculator then returns the gap as a quick summary of the balance between measured and unmeasured ions.
What does a high anion gap indicate?
A high anion gap usually suggests excess unmeasured acids from an acid load, which often suggests metabolic acidosis. Typical causes include lactate acidosis, ketoacidosis, renal insufficiency, and poisoning. The result is a clue that should be interpreted alongside symptoms, kidney function, and other chemistry findings.
Should the anion gap be corrected for albumin?
Yes, correction for albumin can be very helpful when albumin is low. Since albumin is a major negatively charged protein, low levels can make the anion gap appear falsely low. A corrected anion gap may give a more accurate picture of acid-base status, especially when there is suspected acidosis or unexplained abnormalities in the electrolyte panel.
How reliable is an Anion Gap Calculator?
An Anion Gap Calculator is generally precise for the arithmetic calculation, but its usefulness depends on the quality of the input and the broader clinical interpretation. It can accurately compute the number from laboratory values, but it cannot determine the cause of an abnormal result on its own. Accuracy also depends on whether the calculator accounts for the albumin level, uses the correct expected range, and reflects the same method as the lab report. For that reason, it is best used for medical guidance, not as a substitute for medical evaluation.